

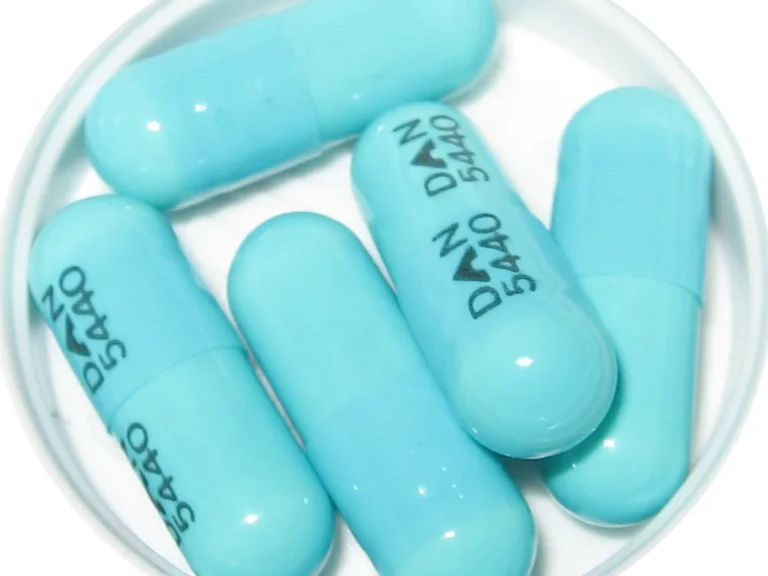

The safety profile of the commonly prescribed doxycycline antibiotic pregnancy loss risk during early gestation has been conclusively illuminated by the largest pharmacoepidemiologic investigation to date, published in the Annals of Internal Medicine. Examining pregnancy outcomes among more than 224,000 individuals, researchers identified that taking doxycycline during the first trimester was associated with an approximate 30% higher risk of spontaneous pregnancy loss. The landmark findings prompt clinicians worldwide to reconsider antibiotic selection in reproductive-aged women.
Broad Clinical Utilization and First-Trimester Vulnerability
Doxycycline is an inexpensive, broad-spectrum semisynthetic tetracycline antibiotic synthesized in the 1960s. Valued for its robust bioavailability and deep tissue penetration, it serves as frontline antimicrobial therapy for a wide range of indications, including acute respiratory tract infections, chlamydia, Lyme disease, and chronic dermatologic conditions such as moderate-to-severe acne vulgaris and rosacea. Tens of millions of outpatient prescriptions are filled globally each year.

Historically, tetracyclines have been strictly contraindicated during the second and third trimesters of human gestation due to their affinity for calcium, which causes permanent brown-gray discoloration of primary dentition and reversible suppression of fetal fibula bone growth. However, evidence regarding early embryonic exposure in the first trimester remained historically equivocal and underpowered, leading many clinical guidelines to tolerate brief courses when perceived benefits outweighed risks.
Much like recent breakthroughs in pharmacological research reveal previously unrecognized systemic consequences of established drugs, large-scale multi-database analytics have now quantified the true gestational risks of first-trimester doxycycline exposure.
A Multi-Database Cohort of 224,870 Pregnancies: Methodological Rigor
The investigation was spearheaded by first author Dr. Almut Winterstein, professor and chair of pharmaceutical outcomes and policy at the University of Florida College of Pharmacy, in collaboration with epidemiologists from the U.S. Centers for Disease Control and Prevention (CDC). The multi-center team interrogated two massive healthcare claims repositories—the MarketScan Commercial Database and Medicaid Analytic eXtract—spanning a twenty-year surveillance period.
Researchers evaluated 224,870 completed pregnancies among females aged 12 to 55 years. More than 218,230 patients were treated for bacterial respiratory tract infections, and over 6,630 were treated for inflammatory acne between estimated conception and the conclusion of the first gestational trimester (14 weeks). Approximately 4,385 women received oral doxycycline, while the remaining cohort received alternative pregnancy-compatible antibiotics (amoxicillin, cephalosporins, or azithromycin).
To circumvent confounding by indication (where the underlying maternal illness rather than the drug induces pregnancy complications), investigators compared doxycycline users exclusively against active controls treated for identical clinical conditions. Multivariable adjustment established that first-trimester doxycycline use carried a 29% heightened risk of pregnancy loss (adjusted odds ratio aOR = 1.29, 95% confidence interval 1.12 to 1.48).
The massive statistical power of the multi-database cohort permitted distinct sub-analyses evaluating miscarriage (pregnancy loss before 20 weeks) versus stillbirth (fetal demise after 20 weeks). While miscarriages comprised the overwhelming majority of documented adverse events, both endpoints exhibited consistent hazard increases associated with first-trimester exposure.
«I would advise physicians to carefully consider the benefit-risk balance when prescribing doxycycline to women who are pregnant or planning a pregnancy. For less-serious routine infections, safer alternatives are readily available.»
Dr. Almut Winterstein, lead author and drug safety researcher, University of Florida College of Pharmacy
Pathophysiological Mechanisms: Trophoblast Disruption and Mitochondrial Stress
How does a tetracycline molecule disrupt early gestational development? Writing in the Annals of Internal Medicine, researchers outline two plausible, biologically validated mechanisms corroborated by preclinical animal models.
The primary pathway involves interference with early placental maturation. As noted by clinical pharmacologist and associate professor Luke Grzeskowiak from Flinders University in Adelaide, Australia, doxycycline acts as a potent inhibitor of matrix metalloproteinases (MMPs). MMP inhibition impairs extravillous trophoblast migration and remodeling of maternal uterine spiral arteries, resulting in placental ischemia and secondary embryonic detachment.
The second potential mechanism involves direct organogenesis toxicity. Because tetracyclines disrupt bacterial ribosomes—which share structural homology with eukaryotic mitochondrial ribosomes—the drug can inhibit mitochondrial protein synthesis in rapidly proliferating embryonic blastomeres, precipitating oxidative cellular apoptosis.
The twenty-year multi-database cohort provided statistical power to distinguish medication risks from underlying illness.
First-trimester exposure correlated with a statistically significant increase in spontaneous miscarriages and stillbirths.
Doxycycline inhibits matrix metalloproteinases essential for spiral artery remodeling and trophoblast invasion.
Long-term acne therapy in reproductive-aged females warrants active pregnancy screening and contraceptive counseling.
The Challenge of Unrecognized Pregnancy in Outpatient Dermatology
The findings hold profound implications for outpatient dermatologic management. Doxycycline is frequently prescribed for two-to-three-month maintenance courses for young, sexually active females with cystic acne. Because roughly 45% of pregnancies worldwide are unplanned, patients frequently continue daily medication regimens through the critical fourth to sixth weeks of gestation before realizing conception has occurred.
Spontaneous pregnancy loss—encompassing miscarriages prior to 20 weeks and stillbirths thereafter—inflicts severe emotional and physical distress. While baseline pregnancy loss affects approximately one in four conceptions due to spontaneous chromosomal aneuploidies, eliminating avoidable pharmacologic teratogens remains an essential preventive mandate.
Maternal-fetal medicine specialists urge prescribers to routinely query pregnancy intention and recommend reliable dual contraception prior to initiating extended courses of doxycycline in reproductive-aged patients.
- Doxycycline use during the first trimester is associated with an adjusted 29% increase in pregnancy loss odds.
- Active-comparator design confirmed the risk is independent of maternal infection indication.
- Pharmacologic inhibition of matrix metalloproteinases and mitochondrial respiration explains the observed biological harm.
- Clinicians managing acne and routine respiratory infections should prioritize safer penicillins and cephalosporins.
Clinical Practice Recommendations: Balancing Risks and Therapeutic Alternatives
Study authors emphasize that clinicians should not reflexively abandon doxycycline in severe or life-threatening scenarios. In acute infections such as Rocky Mountain spotted fever, anthrax, or refractory Lyme disease with neuroborreliosis, doxycycline remains uniquely life-saving, and untreated maternal systemic infection presents far greater fetal peril.
However, for mild-to-moderate respiratory infections, sinusitis, or acne vulgaris, safer, highly effective antimicrobial substitutes exist. Beta-lactam agents (such as amoxicillin-clavulanate or cephalexin) maintain decades of reassuring obstetric safety profiles.
The research by Winterstein and colleagues delivers an urgent clinical reminder: prescribing decisions in reproductive-aged females require deliberate consideration of gestational status to safeguard early maternal and embryonic health.